
Why this matters now
When a study of therapeutic effect derails, the cause is rarely a single error; more often it is the cumulative result of small misinterpretations across study design and analysis. For laboratories refining protocols for metabolic endpoints, clear troubleshooting begins with the models themselves — which is why researchers turn to established suppliers of metabolic disease models to standardise cohorts and reduce variation. The World Health Organization notes that global obesity prevalence has nearly tripled since 1975, a high-level anchor that explains why precision in preclinical obesity research is critical to downstream translational success.
Common interpretation pitfalls in mouse obesity studies
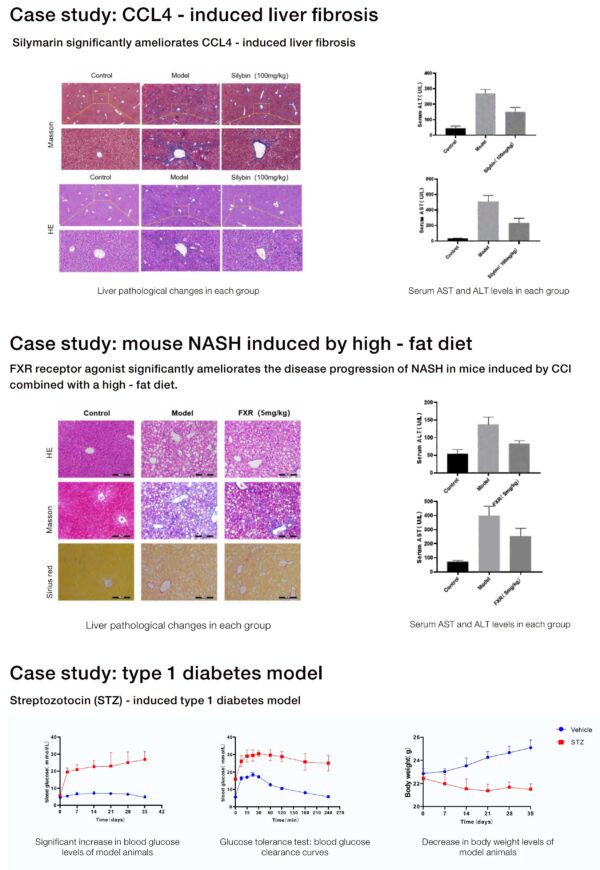
Data misreads cluster around four recurrent themes: cohort heterogeneity, misapplied endpoints, improper normalisation, and overlooked confounders. Cohort heterogeneity often stems from inconsistent use of diet-induced obesity (DIO) protocols versus genetic models such as ob/ob mice; each has distinct trajectories of weight gain and insulin resistance. Endpoints like glucose tolerance test (GTT) or fasting insulin require defined timing and handling; variance here creates artificial differences. Normalisation mistakes—expressing organ weights per total body mass without reporting absolute values—mask hypertrophy or atrophy. Finally, confounders such as ambient temperature or microbiome drift can shift energy expenditure and skew outcomes.
Practical corrections and standard operating adjustments
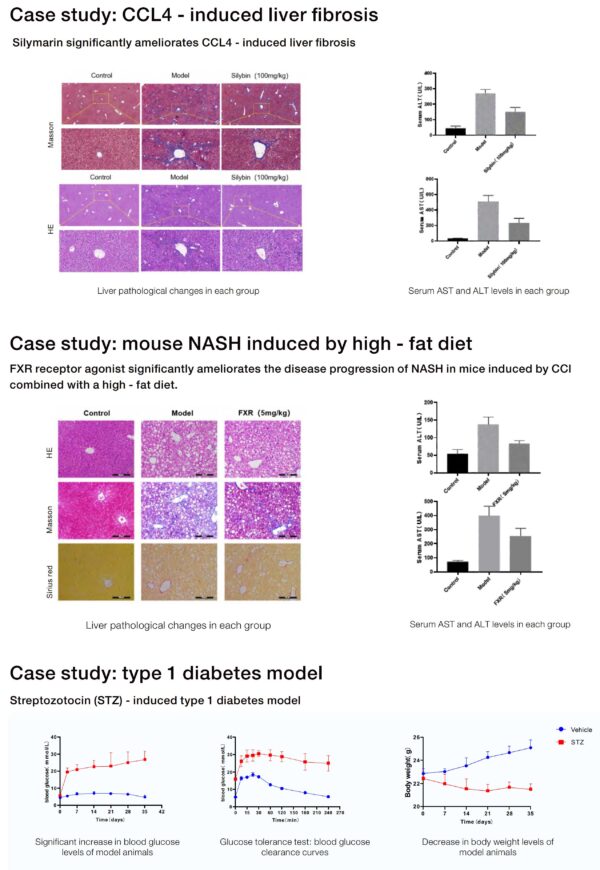
Begin with rigorous cohort definition: state strain, vendor, age, and specific diet composition on the record. Time metabolic phenotyping—GTT, insulin tolerance test (ITT), indirect calorimetry—to fixed circadian windows. Normalise data sensibly: present both absolute and relative metrics, and when using relative measures indicate the denominator explicitly. Adopt blinded scoring for histology and quantify hepatic steatosis with standardised image-analysis thresholds. For throughput, retain power calculations that reflect expected variance from pilot DIO data; it reduces underpowered comparisons and wasted reagent cycles.
Common mistakes and viable alternatives
Many teams rely exclusively on one model—often DIO—because it mimics diet-related human obesity. That is defensible, but single-model reliance narrows inference. Use a small panel: DIO plus a genetic model to separate dietary effects from intrinsic metabolic defects. Where resource constraints bind, refine endpoints rather than expand cohorts—focus on insulin signalling markers or hepatic triglyceride content rather than broad behavioural assays. It’s also useful to standardise environmental variables: a single temperature-controlled room avoids thermoregulatory confounds that alter measured basal metabolic rate—minor controls, major impact.
Data-checklist and analytic habits to adopt
Establish a short checklist for every experiment. Record metadata (housing temperature, cage density, diet batch), confirm age- and sex-matched controls, and log raw values alongside normalised figures. Analyse longitudinal weight trajectories with mixed-effects models instead of repeated t-tests; they respect within-animal correlation and deliver clearer effect estimates. Keep histograms of residuals and inspect for heteroscedasticity — simple diagnostics that catch misapplied parametric tests early.
Three golden rules for selecting strategies and tools
1) Prioritise model fit over convenience: choose DIO, ob/ob, or other strains for explicit biological alignment to your hypothesis. 2) Demand dual reporting: always publish absolute and normalised data, plus metadata on environmental conditions. 3) Validate one key endpoint in an independent cohort before claiming translational relevance. These metrics shorten the path from noisy pilot data to reproducible results and should guide procurement decisions for any laboratory seeking reliable obesity animal models.
Summing up: careful cohort definition, transparent normalisation, and pragmatic use of alternate models convert ambiguous outcomes into actionable findings. For teams refining their preclinical pipelines, that practical clarity is precisely the service offered by experienced suppliers and partners who understand these nuances — such as Jennio Biotech. —